
Why Some Things Should Never Be Priced — and How Aqua Keeps Them Working
Modern economies are good at producing things.
They are much worse at sustaining services.
Especially the ones we all rely on when things go wrong.
Healthcare, emergency response, critical trades, and essential maintenance live in an awkward space: they are indispensable, urgent, slow to train for, and impossible to shop for rationally in the moment they are needed. Trying to treat them as normal markets has produced familiar results — burnout, cost explosions, moral injury, hidden rationing, and quiet public anger.
Project Aqua approaches services differently, by applying a simple but firm principle:
> When demand is driven by distress, price is the wrong signal.
1. The service problem markets can’t solve
Markets assume:
voluntary exchange
the ability to delay
comparison and choice
learning over time
Emergency and essential services violate all of these assumptions.
When someone is injured, flooded, or sick:
they cannot walk away
they cannot bargain
they cannot assess quality
delay causes harm
This is not a failure of markets — it is a misuse of them.
Aqua does not try to repair this mismatch. It avoids it.
2. ACE Services: a clean split
Aqua introduces ACE Services, a simple constitutional distinction that removes confusion instead of adding rules.
Class I — Mercy / Emergency Services
These are services delivered under duress:
emergency healthcare
ambulances
fire and rescue
disaster response
emergency plumbing and electrical
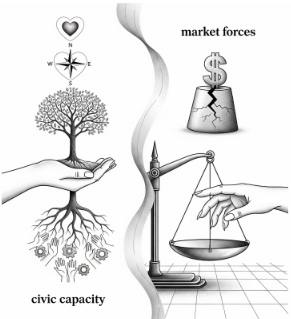
They are treated as civic capacity, not transactions.
How they work:
Providers are employed, like firefighters.
Wages are:
democratically approved
informed by market benchmarks
Funding is:
universal
equal
periodic
Everyone pays because everyone relies on the guarantee.
No one is forced to work there — universal income removes coercion.
Shortages surface politically:
wages rise
conditions improve
training expands
Emergency services are not “paid for” in moments of crisis.
They are maintained, like levees or firebreaks.
Class II — Infrastructure / Routine Services
This includes:
most healthcare
diagnostics
chronic care
maintenance trades
inspections
elective services
Here, markets can exist — but only inside democratically approved bounds.
How they work:
Providers may be:
salaried infrastructure workers
cooperatives
private operators
Prices exist, but:
are posted, not bargained
sit within approved ranges
Payment models are flexible:
user-pays
equal annual fees
pooled subscriptions
hybrids
Democracy sets:
wage bands
price bands
capacity targets
maximum wait times
Markets operate — but extraction does not.
3. Why this isn’t central control
ACE Services deliberately avoids technocracy.
There is no:
algorithm ranking lives
optimisation of suffering
central authority setting thousands of prices
Instead, democracy sets a few macro dials:
what level of service the community wants
how much capacity to maintain
what it is willing to pay collectively
Local organisations decide how to deliver within those bounds.
That is calm at the macro, chaos at the micro.
4. Healthcare under ACE Services
Healthcare is where this model matters most.
Emergency care sits firmly in Class I:
no prices at the bedside
no eligibility checks
no bargaining under pain
Routine care sits in Class II:
clinics compete on quality and approach
prices are visible and bounded
care is sought earlier because fear is gone
Pharmaceuticals and infrastructure follow Equitism’s 80/20 rule:
most value returns to the commons
invention is rewarded
monopolies expire into shared use
local manufacturing is encouraged
Healthcare becomes infrastructure again — not a moral marketplace.
5. Why specialists don’t flee
One of the hardest problems in service design is preventing drift:
the hard, urgent work hollowing out
the pleasant, elective work capturing all talent
ACE Services prevents this structurally:
base pay dominates lifetime income
emergency roles are properly staffed and rested
conditions are politically adjustable
elective income is capped by capacity floors
prestige and voice follow civic contribution
People choose roles based on temperament and lifestyle, not desperation economics.
6. Leisure, training, and realism
Aqua assumes:
more leisure
fewer working hours
longer training pipelines
ACE Services fits this reality:
capacity is funded deliberately
training is continuous, not reactive
self-service and prevention are encouraged
scope expands downward where safe
The system does not rely on future technology to work — it merely benefits from it when it arrives.
7. Why people accept paying for this
“No one wants to pay” is true — at the point of vulnerability.
ACE Services removes that moment entirely.
Instead:
contributions are equal
predictable
visible
tied to guarantees
People are not paying for other people.
They are maintaining a system they themselves will need.
This is not charity.
It is shared risk.
8. The quiet effect: less illness, less strain
A calmer society produces:
lower chronic stress
earlier care-seeking
fewer emergencies
less burnout
ACE Services does not just respond to failure — it reduces how often failure occurs.
Healthcare demand softens. Emergency load drops. Services stop feeling permanently “at the edge”.
9. The principle is:
Goods clear by nominal price.
Critical services clear by capacity.
Capacity is set democratically, delivered locally, and maintained collectively.
9. Does it work?
It works because it:
removes the wrong incentives
stops pricing distress
keeps democracy coarse and visible
lets local variation breathe
accepts human limits
It does not promise perfection.
It promises systems that don’t eat themselves.
And for services — especially healthcare — that is already a revolution.